
Agent Kelly: Rethinking US Healthcare Scheduling
Agent Kelly predicts patient no-shows with 87% accuracy, refills cancelled slots and recovers 12% to 18% of clinic revenue, inside your EHR and your cloud.
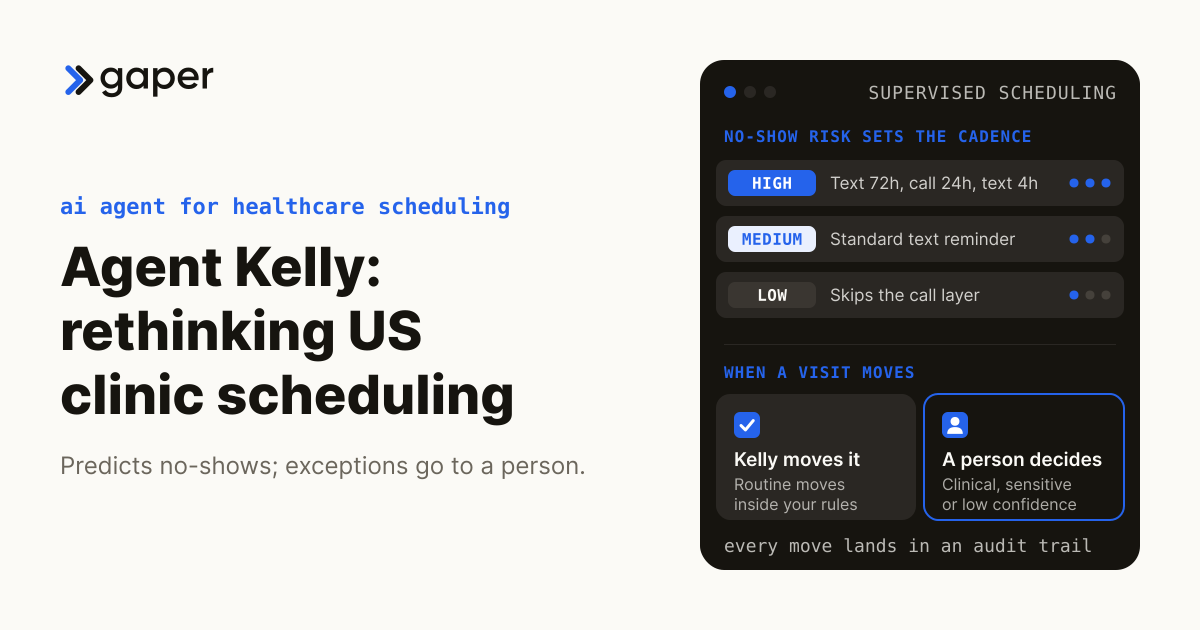
Agent Kelly is the Gaper AI agent for healthcare scheduling and patient intake: it predicts which patients will miss a visit with 87% accuracy, confirms and refills slots, and routes anything clinical or sensitive to a person. Mid-market clinics recover 12% to 18% of revenue lost to no-shows and unfilled cancellations, roughly $250,000 to $500,000 a year for a 6-provider practice. Kelly plugs into the EHR you already run and is deployed in your cloud.
Agent Kelly is out to change US healthcare scheduling in 2026
Agent Kelly is the Gaper.io AI agent built for healthcare scheduling, intake, and patient reminders. The agent predicts no-shows with 87% accuracy, fills cancelled slots automatically, and recovers 12% to 18% of typical revenue leakage in mid-market clinics. Setup runs 1 to 2 weeks against existing EHR systems.
Key Takeaways
- Healthcare clinics lose 12% to 18% of revenue to no-shows, late cancellations, and unfilled gaps.
- Agent Kelly predicts no-show risk with 87% accuracy and triggers smart confirmations before the visit.
- Typical clinic onboards in 1 to 2 weeks against existing EHR systems with no clinical workflow change.
- Mid-market clinics report 30% to 40% scheduler time savings and 12% to 18% revenue recovery.
- Kelly runs in your cloud on your auth, with SSO, role-based access, PII handling and audit logs, and anything clinical or sensitive goes to a person.
Table of Contents
- Meet Agent Kelly
- Why is healthcare scheduling broken today?
- How does Agent Kelly predict no-shows with 87% accuracy?
- Agent Kelly vs. legacy scheduling systems
- How do clinics roll Kelly out?
- How does Gaper transform healthcare scheduling with AI agents?
- What results should clinics expect?
- Buyer questions: EHR, go-live, accuracy, price and staff
Meet Agent Kelly
Agent Kelly is the Gaper.io AI agent for healthcare scheduling. It handles patient intake, appointment booking, no-show prediction, slot recovery, and pre-visit reminders. Kelly works alongside your front-desk team, not in place of them. Schedulers stop spending hours on confirmation calls and instead handle the exceptions Kelly escalates.
Kelly is one of four Gaper AI agents in production in 2026, alongside AccountsGPT for accounting firms, James for HR recruiting, and Stefan for marketing operations. Each agent ships pre-built for a vertical and customizes against the client's specific systems in 1 to 2 weeks.
What Kelly handles, and what it routes to a person
The Agent Kelly product page sets out four jobs. Kelly collects and validates intake details into your systems, so nobody rekeys a clipboard form. It answers routine patient questions from your approved content, with citations. It books, reschedules and confirms appointments against your calendar rules. And it hands clinical or sensitive cases to a person, with the full context of the conversation attached.
Kelly does not make clinical decisions. Whether a symptom can wait until next week is a clinical question, so it goes to your staff; moving a Tuesday follow-up to Thursday is a scheduling question, so Kelly handles it inside your rules. For the intake side, our piece on whether Agent Kelly can handle patient intake better than front desk staff walks through it.
Why is healthcare scheduling broken today?
Scheduling runs on phone calls, EHR portals and text reminders that do not talk to each other, and none of them predicts who will miss a visit. No-shows and late cancellations leave paid capacity empty, and across mid-market clinics that leakage costs 12% to 18% of revenue.
The result is predictable revenue leakage. Published no-show rates vary widely by specialty and population: a systematic review of 105 studies in Health Policy (Dantas and colleagues, 2018) put the worldwide average at about 23% (study), and a study of ten main clinics at a large Veterans Affairs medical center in Houston found a mean of 18.8% over fiscal years 1997 to 2008 (BMC Health Services Research, 2016). Cancellations add to the gap. MGMA's 2025 DataDive benchmarks report a 19.95% appointment cancellation rate for single-specialty practices in 2024, and only 27.40% of cancelled visits were rescheduled within 30 days (MGMA Stat, August 2026).
The problem is not shrinking: in MGMA's 11 August 2026 poll, 32% of medical groups said no-shows were higher than in 2025, 58% about the same and 10% lower (same source). At a 12% to 18% revenue leak, a 6-physician practice billing $4M annually loses $480,000 to $720,000 per year to these gaps.
The same VA study put the average cost of one no-show at $196 in 2008 dollars, which is dated, so run the number against your own average visit revenue.
No-show prediction accuracy across methods
| Method | How it works | Accuracy |
|---|---|---|
| Random guessing baseline | Coin-flip floor for any binary prediction. | 50% |
| EHR rules-based reminders | Standard "remind everyone 24 hours out" approach in most EHRs. | 70% |
| Agent Kelly ML model | Per-clinic prediction trained on 12 to 24 months of visit history. | 87% |
Accuracy above 85% is the threshold where automated confirmation routing meaningfully beats human-only outreach. Kelly clears that bar by the end of week two of training.
The hidden cost of manual confirmations
Confirmation calls, rescheduling, and intake paperwork take a large share of every front-desk day. That work does not generate revenue, it just preserves the revenue already booked. The people doing it are also hard to keep: in MGMA's May 2025 poll, 29% of medical groups reported higher staff turnover, and front-office roles were among the most cited hotspots (MGMA Stat, May 2025). When a scheduler leaves, the calls pile onto whoever is left, so the bottleneck becomes operational rather than clinical.
Reminders work, which is why the load is worth automating rather than dropping. A 2013 Cochrane review found text reminders raised attendance from 67.8% to 78.6% against no reminder, about the same effect as a phone call, at a lower cost per attendance (Cochrane, 2013). The cheap channel does most of the work, so calls are worth saving for the patients most likely to miss.
Why portals do not solve the problem
Patient portals shift work to the patient, which works for tech-comfortable populations but fails for many older patients and for anyone who never logs in. Nationally, 77% of individuals were offered online access to their records or a portal in 2024, but only 65% were offered access and used it at least once in the past year (ONC Data Brief No. 77, 2025). That leaves about a third of patients outside the channel. The portals do not predict who will no-show, they do not automatically refill cancelled slots, and they do not learn from history. Kelly does all three.
How does Agent Kelly predict no-shows with 87% accuracy?
Kelly trains a separate model for each clinic on 12 to 24 months of visit history, per-patient behavior and outside signals such as weather and day of week. It retrains weekly as new outcomes arrive, so the risk score reflects your patients rather than a national average.
Agent Kelly trains a per-clinic prediction model on three sources of data. Historical visit records, typically 12 to 24 months of past appointments. Per-patient behavior patterns covering cancellation rate, lead time, and response to confirmations. External signals such as weather, day of week, and seasonality. The model retrains weekly as new visit outcomes flow in.
Where annual revenue lands at a typical 6-physician clinic
| Revenue line | Share of annual revenue |
|---|---|
| Captured revenue | 82% |
| No-show loss | 12% |
| Cancellation loss | 6% |
Two thirds of every clinic's annual leakage is no-shows. Kelly targets the no-show line first because the prediction confidence is higher than for late cancellations.
Inputs the model uses
Patient age, distance to clinic, insurance type, prior no-show rate, appointment lead time, provider, time of day, day of week, and weather forecast for the appointment date. The model weighs these inputs against historical outcomes for similar patient-appointment combinations.
Those inputs line up with the research. The 2018 Health Policy review found long lead time and prior no-shows were the strongest predictors, with younger adult age, lower socioeconomic status, distance from the clinic and no private insurance also raising risk. A flat reminder rule sees none of that.
How predictions feed the workflow
High-risk appointments trigger a multi-channel confirmation sequence with text at 72 hours, a phone call at 24 hours, and a final text 4 hours before. Medium-risk gets a standard text reminder. Low-risk skips the call layer to save scheduler time. The result is fewer calls overall, down 60% in typical clinics, and a measurably higher confirmation rate for the high-risk appointments that actually need attention.

On privacy, HHS guidance says the Privacy Rule lets providers contact patients about their care, including messages left on an answering machine, though the message should reveal as little as possible, for example only the practice name, a call-back number and what is needed to confirm the appointment (HHS HIPAA FAQ 198). State law can be stricter, so your compliance lead sets the wording Kelly uses. This is information, not legal advice.
Does Kelly overbook high-risk slots?
Kelly books against your calendar rules, so whether a high-risk slot is double-booked is a rule your practice sets, not a decision the agent makes on its own. A sensible start is confirmations and slot recovery only, adding an overbooking rule once the risk scores have earned your team's trust.
There is a case for it. A study on 104,799 visits at a pediatrics clinic used a no-show model to overbook only the appointments predicted to be missed; in simulation that cut patient waiting by about 6% to 9% and overtime by roughly a quarter against even or random overbooking (Applied Clinical Informatics, 2014). It was not tested prospectively, so confirm first, refill from the waitlist second, and overbook last.
Agent Kelly vs. legacy scheduling systems
Most US clinics already pay for a scheduling module inside their EHR or a standalone scheduling SaaS. These systems are functional but rarely predictive. Kelly differs on three dimensions.
| Capability | EHR scheduling module | Standalone scheduling SaaS | Agent Kelly |
|---|---|---|---|
| No-show prediction | None | Basic rules | 87% accuracy ML model |
| Automatic slot recovery | Manual only | Waitlist push | Predictive + outreach |
| Confirmation cadence | Fixed | Configurable | Per-patient risk tier |
| Setup time | 6 to 12 months | 4 to 8 weeks | 1 to 2 weeks |
| Per-clinic customization | Limited | Templates | Custom model per clinic |
| Annual cost (6 providers) | $12k to $40k | $8k to $20k | $24k to $36k including build |
Setup and cost ranges for EHR modules and standalone SaaS are typical ranges, not vendor list prices. Ask your own vendors for a quote before comparing.
Kelly fits between the EHR module and the standalone SaaS. It runs on the predictive intelligence the EHR lacks, with the workflow customization the SaaS cannot match. The result is faster setup and a model tuned to your specific clinic, not a templated configuration shared across thousands of practices.
There is also an honest case for not using Kelly. If your EHR's reminders already hold no-shows low and cancellations refill the same day, the module you pay for is enough. Our guide to build vs buy for AI agents sets out the test: buy a product when the workflow is standard and the data path is simple, and own a custom agent when integration, compliance or control decide the outcome.
What Agent Kelly is not
Kelly is not an EHR replacement. It plugs into your existing Epic, Athenahealth, or eClinicalWorks setup and pulls schedule data through the standard FHIR or HL7 interfaces. Kelly is not a marketing tool either. It does not handle new-patient acquisition, only the scheduling and retention of patients already in your system.
How Kelly connects to your EHR
Kelly is wired into your EHR and the tools around it, such as your text and phone provider, and works in the system of record rather than beside it. The FHIR route is widely available: certified health IT developers had to give customers FHIR-based APIs under ONC's Cures Act Final Rule by 31 December 2022, and ONC reported more than 95% met the deadline (ONC, February 2023).
One caution for your IT lead: the certified API standard covers read services and excludes write capabilities (ONC, criterion 170.315(g)(10)). Writing a booked or moved appointment back depends on what your EHR vendor exposes, so confirm write access in week one.
Patient data, HIPAA and the BAA
Kelly is HIPAA-aware and deployed in your cloud, on your auth, with SSO, role-based access, PII handling and audit logs, so patient data stays inside your boundary. Gaper's AI automation for healthcare page states that deployments carry encryption and a signed BAA, and that a security review runs before anything reaches production.
The BAA matters because the law requires it. Under HIPAA, a practice may share protected health information with a business associate only after getting satisfactory assurance that the vendor will safeguard it, documented in a written contract or other written arrangement that meets 45 CFR 164.504(e) (45 CFR 164.502(e)). Ask any scheduling vendor: will you sign a BAA, where does patient data sit at rest, and does any of it leave our environment? Our guide to AI agent security covers the controls in more detail.
How do clinics roll Kelly out?
Most 6-provider clinics are fully on the new flow inside 2 weeks. Multi-site practices typically take 3 to 4 weeks to roll out across locations.
The build team is typically a vetted AI engineer plus a full-stack engineer from Gaper. The Python developer owns the model training pipeline and the FHIR integration.
What happens in each week
Week 1 covers EHR integration and historical data ingestion, which is where the 12 to 24 months of visit history the model trains on comes in. Week 2 covers shadow-mode calibration followed by go-live.
Underneath is the method on the Kelly page: map the workflow, build the supervised agent with evaluations and guardrails, connect your stack, then launch in a sandbox and move into supervised production with traces, rollback and an owner. At handover you own the code, runbook and evaluation suite.
How a person stays in the loop on rescheduling
Routine moves inside your rules, such as shifting a follow-up to another open slot with the same provider, Kelly handles on its own. Anything outside the rules, anything clinical or sensitive, and any case where Kelly's confidence is low goes to a scheduler with the context attached. Every interaction lands in an audit trail, so a practice manager can see what Kelly did.
Start narrow and widen what Kelly does alone as the audit trail builds trust. Our guide to human-in-the-loop AI explains how approval gates and confidence thresholds decide what an agent ships and what a person checks.
How does Gaper transform healthcare scheduling with AI agents?
Beyond Kelly, Gaper supports the broader operational stack a clinic needs to run sustainably. This includes intake automation, prior authorization handling, and care-team coordination tooling. Most clinics start with Kelly for the immediate revenue recovery and expand to other agents over the following 6 to 12 months.
Gaper is the AI-native implementation partner that deploys supervised AI agents you own. The wider set of healthcare workflows, from eligibility and prior authorization to claims and credentialing, is on our AI agents for healthcare page.
For broader context on AI replacing routine operational work in healthcare, see our analysis of jobs AI will replace by 2030. Front-desk roles are not eliminated, they are repositioned toward higher-value patient interaction.
What results should clinics expect?
Within 90 days of go-live, mid-market clinics typically recover 12% to 18% of lost revenue, save 30% to 40% of scheduler time, cut confirmation calls by 60%, and see patient survey scores rise by 8 to 15 points.
Typical mid-market clinics see results in three areas within the first 90 days of Kelly going live.
Kelly results in the first 90 days post go-live
| Metric | Change |
|---|---|
| Revenue recovered | 12% to 18%, up |
| Scheduler time saved | 30% to 40%, up |
| Patient survey score | +8 to 15 points |
| Confirmation calls | 60%, down |
All four metrics move in the same direction inside 90 days. The 60% drop in confirmation calls is the leading indicator that the scheduler time savings will show up in payroll the following quarter.
Revenue recovery
Clinics recover 12% to 18% of previously lost revenue from no-shows and unfilled cancellations. For a 6-provider practice this is typically $250,000 to $500,000 per year, compared to a Kelly cost of $24k to $36k.
To size your own gap, add last year's no-shows to the late cancellations that were never refilled, and multiply by your average revenue per visit.
Scheduler time savings
Front-desk teams save 30% to 40% of their time, which gets redirected toward patient experience, billing follow-up, and reducing the call queue. Most clinics report fewer scheduler hires needed during growth periods.
Patient satisfaction
Patient survey scores rise by 8 to 15 points on average. The drivers are shorter call queues, fewer missed appointments where Kelly's predictive layer surfaces gaps proactively, and easier rescheduling. The satisfaction lift comes from removing friction rather than adding features.
Ready to recover 12% to 18% of clinic revenue with Agent Kelly?
Bring last year's no-show and cancellation numbers to a free AI assessment. Free assessment, no commitment: we map your scheduling workflow, size the gap, and tell you honestly whether your current EHR module is enough.
Does Agent Kelly require replacing our EHR?
No. Kelly connects to Epic, Athenahealth, eClinicalWorks, and other major EHRs through standard FHIR or HL7 interfaces. Your clinical workflow does not change. Kelly only adds the scheduling intelligence and confirmation automation layer on top of what you already have.
How fast can a 6-provider clinic go live?
Most 6-provider clinics go live in 1 to 2 weeks. Week 1 covers EHR integration and historical data ingestion. Week 2 covers shadow-mode calibration followed by go-live. Larger practices with multiple locations typically need 3 to 4 weeks for the rollout across sites.
Two things outside the build can set the pace: how quickly your EHR vendor grants the interface access and whether your visit history is clean enough to train on, so start those two conversations before the kickoff.
What is the realistic accuracy on no-show prediction?
Kelly reaches 85% to 89% accuracy on no-show prediction after the first 2 weeks of training against the clinic's historical data, about 87% on average, compared with around 70% for standard EHR rules-based reminders.
Accuracy is highest for patients with 3 or more prior visits in the data, where Kelly has learned their personal behavior pattern. Accuracy is lower for brand-new patients where the model relies on demographic and appointment-type signals only.
How is Kelly priced for a typical clinic?
For a 6-provider practice, Kelly costs $24k to $36k a year including the build, against $250,000 to $500,000 a year in recovered revenue from no-shows and unfilled cancellations.
That compares with $12k to $40k for a typical EHR scheduling module and $8k to $20k for a standalone scheduling SaaS. For a multi-site group, ask for a number scoped to your own volume.
What happens to our scheduling staff?
Schedulers are not eliminated. Their time shifts from confirmation calls (which Kelly handles automatically) to patient experience, billing follow-up, and reducing the call queue.
Most clinics keep the same scheduler headcount but redirect 30% to 40% of their time to higher-value work. Some clinics use the savings to delay new hires rather than reducing existing staff.
Thirty minutes, no commitment. We map one workflow, make the build or buy call, and scope the smallest thing worth shipping.
Frequently asked questions
Why is healthcare scheduling broken today?
How does Agent Kelly predict no-shows with 87% accuracy?
How do clinics roll Kelly out?
How does Gaper transform healthcare scheduling with AI agents?
What results should clinics expect?
Does Agent Kelly require replacing our EHR?
How fast can a 6-provider clinic go live?
What is the realistic accuracy on no-show prediction?
How is Kelly priced for a typical clinic?
What happens to our scheduling staff?

Ai Healthcare Agents Heal Healthcare System
AI agentsAI Agent Myths vs. Reality: What Enterprise Buyers Get Wrong
A practical breakdown of the most common AI agent myths and the production reality enterprise buyers face when taking agents from pilot to live workflows.
Apr 2, 2026AI agents7 Reasons AI Agent Projects Fail (and How to Avoid Them)
Most AI agent projects die between the demo and production. Here are the seven failure modes that kill them, and the operating decisions that get agents shipped.
Mar 27, 2026Ready to turn AI into execution?
Book a free assessment of one workflow. We map it, make an honest build versus buy call before any code, and if an off the shelf product covers the job we will tell you so.