
AI for Hospitals: What Actually Works in Production (2026)
Which hospital AI works in production in 2026, from scheduling to coding and prior auth, what still needs a clinician, and the EHR, BAA and HIPAA work it takes.
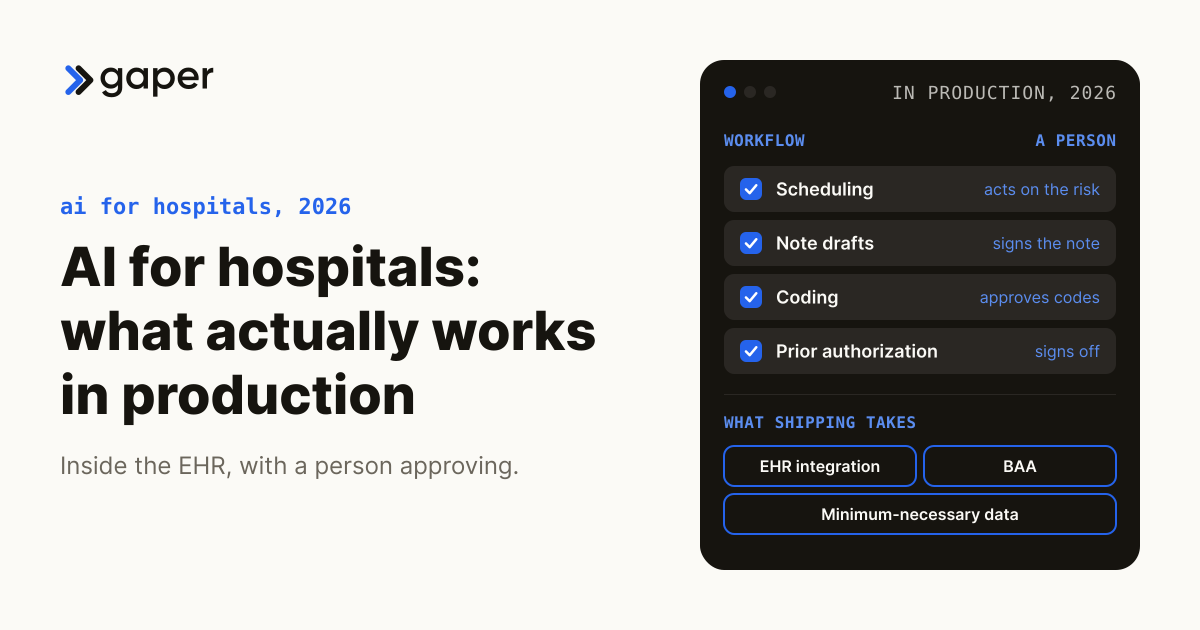
Hospital AI that works in production in 2026 is mostly operational: scheduling, note drafts, coding and prior authorization, inside the EHR, with a person approving anything clinical or financial. Failures automate the wrong process or skip the integration and BAA work.
TL;DR: The AI Reality Check for Hospital Leaders
Not all hospital AI deployments succeed. The winners share three traits: they solve a specific, measurable problem (reducing no-shows or documentation time), they integrate with existing EHR systems rather than replace them, and they have strong clinical and operational leadership backing implementation. The biggest failure mode remains the same: buying AI to automate the wrong process, or trusting vendor claims without asking for pilot data first.
Contents
- The 7 applications that work
- Connecting AI to the EHR
- Clinical NLP and custom LLMs
- Costs and compliance
- Prior authorization dates
- How Gaper helps
OUR ENGINEERS BUILD HIPAA-COMPLIANT AI FOR TEAMS AT
Hospitals, Health Systems, Health Plans, Life Sciences, and Revenue Cycle Operations
Ready to Deploy Hospital AI?
Get a free AI assessment from our healthcare engineering team. See the workflows we build on our AI agents for healthcare page.
What Is Hospital AI?
Hospital AI is software that learns patterns from clinical, operational or financial data to automate a task, predict an outcome or recommend an action to a person who decides. In 2026 most of it runs inside the EHR, and a clinician or staff member still owns the decision.
Hospital AI rarely makes the final decision alone, and that is not a weakness: licensing rules keep a clinician accountable, FDA's device rules turn partly on whether a professional can review a recommendation's basis, and clinicians catch context algorithms miss. Our guide to human-in-the-loop AI explains approval gates.
The State of AI Adoption in US Hospitals (2026 Update)
In 2024, 71% of non-federal acute care hospitals used predictive AI integrated into their EHR, up from 66% in 2023 (ASTP/ONC Data Brief No. 80, September 2025). Adoption is uneven: 86% of system-affiliated hospitals against 37% of independent ones, and 50% of critical access hospitals against 80% of others. Among users, 82% evaluated models for accuracy, 74% for bias and 79% monitored them after go-live.
Why Hospitals Are Different from Other Industries
Software that analyzes medical images or signals, or whose reasoning a clinician cannot independently review, can be a regulated device under FDA oversight. HIPAA governs every use of patient data. Margins are thin: the National Hospital Flash Report on August 2026 data says nearly half of hospitals are in the red (Kaufman Hall, published by Vizient). And clinical buy-in, not technology, is often the limiting factor.
The 7 Hospital AI Applications That Actually Work in 2026
For each: what is in production, what needs a person, and what shipping takes (nearly always an EHR integration, a BAA and minimum-necessary data).
1. Patient Scheduling and No-Show Prediction
A review of 105 studies put the average no-show rate at about 23% (Health Policy, 2018). AI scheduling systems like Kelly (an AI scheduling agent) predict which patients are likely to miss their appointment based on historical booking patterns, demographics, weather, time of day, and distance to facility. Kelly integrates with existing EHR and scheduling systems and works without requiring clinicians to change their workflow. Upfront cost ranges from $15,000 to $50,000, with annual maintenance around $5,000 to $15,000. ROI is measurable within 2 to 4 months in most cases because the value is immediate and quantifiable: each prevented no-show saves the hospital approximately $150 to $300 in lost revenue and staff time.
- In production: the fastest-growing use; among predictive AI users, scheduling rose from 51% to 67% in a year (ASTP/ONC). Text reminders lifted attendance from 67.8% to 78.6% versus none (Cochrane, 2013).
- Needs a person: anything clinical, and overbooking rules.
- To ship: scheduling read and write access, a BAA, minimal-PHI reminder wording.
2. Clinical Documentation (Ambient Listening)
Ambient AI drafts the note from the visit for the clinician to sign. In a UCLA randomized trial of 238 physicians, Nabla cut time in notes by 9.5% against usual care, Microsoft DAX's change was not significant, and physicians reported occasional clinically significant inaccuracies, mostly omissions (NEJM AI, 2025, via UCLA Health).
- In production: outpatient note drafts written back into the EHR.
- Needs a clinician: every note. Fuller notes do not raise payment by themselves: office E/M levels follow medical decision making or time (CMS E/M Services Guide).
- To ship: a BAA, patient notice under your state's recording law, and a draft audit in the first weeks.
3. Sepsis and Deterioration Early Warning
About 1.7 million US adults develop sepsis each year, and at least 350,000 die in hospital or go to hospice (CDC). Results depend on the model and site: the Epic Sepsis Model scored an AUC of 0.63 at Michigan Medicine (JAMA Internal Medicine, 2021), while patients whose TREWS alert was confirmed within 3 hours had an 18.7% relative reduction in adjusted in-hospital mortality in an observational study (Nature Medicine, 2022).
- In production: EHR-embedded early-warning scores.
- Needs a clinician: every alert; alert fatigue is the main failure mode.
- To ship: validation on your own patients, a named owner per alert, an FDA status check.
4. Radiology AI (Triage and Second Read)
Triage moves a suspected critical finding, such as a hemorrhage, to the top of the worklist; second-read tools flag findings a radiologist may miss. Of the 1,614 devices on FDA's AI-enabled device list, 1,230 (76%) sit under the radiology panel (FDA, current as of 4 September 2026; our count).
- In production: worklist triage and detection aids, each cleared for a specific indication.
- Needs a clinician: the read and the signed diagnosis.
- To ship: a clearance that fits your use, PACS integration, a BAA and drift monitoring; FDA's change control plan guidance governs updates (FDA, revised August 2025).
5. Revenue Cycle Management and Coding
HealthCare.gov insurers denied 20% of in-network claims in 2023 (KFF, updated March 2026). Coding AI helps coders but does not replace them: asked for codes from their descriptions, GPT-4 matched exactly only 33.9% of the time for ICD-10-CM and 49.8% for CPT (NEJM AI, 2024). The working pattern is retrieval against the code set plus a coder who approves each suggestion.
- In production: assisted coding, claim scrubbing, denial triage and appeal drafts; billing use rose from 36% to 61% in a year (ASTP/ONC).
- Needs a person: final codes, every appeal, anything that changes what is billed.
- To ship: access to notes, charges and remittances, a BAA, an approval audit trail.
6. Bed Management and Capacity Planning
Models that predict length of stay, discharge timing and readmission risk inform bed allocation, most usefully in large academic centers.
- In production: predicted discharge dates for patient flow teams; inpatient risk prediction is used by 93% of hospitals running EHR-developer AI (ASTP/ONC).
- Needs a person: discharge decisions and bed assignments.
- To ship: near-real-time admit, discharge and transfer feeds, and accuracy checks by unit.
7. Supply Chain and Inventory Optimization
Demand forecasting uses usage history, surgical schedules and ERP data to set par levels, aiming to reduce waste and emergency purchases.
- In production: forecasts and par-level recommendations inside ERP systems.
- Needs a person: purchasing and substitutions.
- To ship: a clean item master and usually no PHI, which makes it a low-risk start.
Hospital AI Adoption by Department
Shares of hospitals using any predictive AI (ASTP/ONC Data Brief No. 80):
| Department | AI use case | Use in 2024 |
|---|---|---|
| Scheduling / Access | Facilitate scheduling | 67% (51% in 2023) |
| Revenue Cycle | Simplify or automate billing | 61% (36% in 2023) |
| ICU / Inpatient | Predict inpatient risk | 93% of EHR-developer AI users |
| Care Management | Identify high-risk outpatients | 88% of EHR-developer AI users |
| Clinical Decision Support | Recommend treatments | 53% of EHR-developer AI users |
The survey does not cover documentation, radiology or supply chain; ask vendors for a source.

What does it take to connect AI to the EHR?
Three things: an integration path (FHIR APIs for reads, vendor APIs or HL7 interfaces for writes), a signed BAA with every vendor that touches patient data, and a data scope limited to the minimum necessary for the job.
FHIR and write-back. Certified health IT had to offer FHIR APIs by 31 December 2022 (ONC, 2023), but the certified API excludes writes (ONC, 170.315(g)(10)). Write-back depends on what Epic, Oracle Health or your vendor exposes. Start with nightly batch jobs.
The BAA. A hospital may share PHI with a business associate only with satisfactory assurance, in a written contract, that it will be safeguarded (45 CFR 164.502(e)). OpenAI and Anthropic offer BAAs for eligible API use and list which features they cover (OpenAI, Anthropic).
Minimum necessary. PHI must be limited to the minimum necessary, with access set by role (45 CFR 164.502(b) and 164.514(d)). Treatment disclosures are exempt; coding, billing and prior authorization are not. Our guide to AI agent security covers the controls.
How do clinical NLP and custom LLMs work on EHR data?
They read the free text in the record, such as notes, discharge summaries and reports, and turn it into structured data: problems, medications and doses, dates and codes. Most production systems use a general model with retrieval and fine-tune only where that clearly wins.
Clinical NLP sits under five uses: note drafts in your house style, ICD-10 suggestions for coders, extraction into structured JSON (medications, labs and dates, procedures, problem lists), research chart abstraction that coordinators verify, and plain-language patient summaries.
Choosing the model. Options are a hosted model under a BAA, an open-weight model in your cloud, a clinical model such as BioBERT or ClinicalBERT for narrow extraction, retrieval-augmented generation (RAG) over guidelines, or a hybrid. Fine-tuning teaches your terminology; RAG looks up current knowledge without changing the model. See custom vs general-purpose LLMs and cloud LLM platforms.
Preparing the data. De-identify by Expert Determination or by Safe Harbor, which strips 18 identifier types, including names, geography smaller than a state, date elements except year and ages over 89 (45 CFR 164.514(b)). Our earlier EHR guide put a fine-tuning set at 500 to 5,000 well-annotated examples; quality beats volume. Split test sets by patient, not row, and measure against a rules or human baseline.
Keeping it honest. Cite source text for every output, keep outputs as drafts, check performance by age, sex, race and payer, and retrain when accuracy drifts.
What Does NOT Work in Hospital AI
AI Diagnosis Without Physician Oversight
Autonomy works only in narrow, authorized cases, such as IDx-DR, which FDA authorized in April 2018 to screen for diabetic retinopathy without a clinician reading the image (FDA, DEN180001). Broad autonomous diagnosis fails: a clinician stays accountable, and models often fail to generalize across sites. The successful model is decision support.
Chatbots for Triage (The Liability Problem)
Chatbots that triage patients create liability when they route someone wrongly. FDA's 2026 CDS guidance covers clinician-facing software only and sets no policy for patient chatbots (Covington, January 2026). Use chatbots for logistics and approved content, with escalation to a person on anything clinical.
Predictive Models Trained on Biased Data
A widely used algorithm that predicted cost rather than illness rated Black patients healthier than equally sick White patients; fixing it would have raised the share of Black patients flagged for extra help from 17.7% to 46.5% (Science, 2019). Require fairness audits and validate on your own patients.
Full Automation Claims
AI augments staff rather than replaces them: a scribe still needs a physician to sign, and a no-show model needs someone to act. Staff prefer AI that reduces their workload to AI marketed as their replacement.
The Real Costs of Hospital AI Implementation
| Solution Type | Upfront Cost | Annual Cost | ROI Timeline | Risk Level |
|---|---|---|---|---|
| Scheduling AI (like Kelly) | $15,000-50,000 | $5,000-15,000/yr | 2-4 months | Low |
| Clinical documentation | $100,000-500,000 | $50,000-200,000/yr | 6-12 months | Medium |
| Radiology AI | $200,000-1,000,000 | $100,000-300,000/yr | 12-24 months | Medium |
| Sepsis alert system | $200,000-800,000 | $80,000-300,000/yr | 12-18 months | Medium |
| Revenue cycle / coding | $50,000-300,000 | $30,000-150,000/yr | 6-9 months | Low |
| Bed management / capacity | $150,000-600,000 | $75,000-250,000/yr | 9-18 months | Medium |
| Supply chain optimization | $100,000-400,000 | $50,000-150,000/yr | 9-15 months | Low |
| Full EHR integration (multi-module) | $500,000-5,000,000 | $200,000-1,000,000/yr | 18-36 months | High |
The scheduling row is Gaper's pricing for Kelly; the others are planning ranges, not vendor quotes.
Costs rise with bed count, EHR interface access, data maturity, customization, validation and training. The biggest hidden cost is change management: budget 15% to 25% of project costs for training and workflow redesign.
HIPAA, FDA, and Regulatory Compliance
HIPAA for AI Systems
Any AI that processes PHI needs a BAA with each vendor, minimum-necessary access and Security Rule safeguards with auditable logs. A proposed Security Rule update (6 January 2025) would make encryption and MFA largely mandatory; it is not final, and HHS now projects July 2027 (Davis Wright Tremaine, July 2026). Build to it anyway. This is information, not legal advice.
FDA Clearance for AI/ML Medical Devices
Software is not a device if it meets all four non-device CDS criteria in section 520(o)(1)(E) of the FD&C Act. FDA's revised final CDS guidance (January 2026) superseded the 2022 version. Devices reach market by 510(k), De Novo or premarket approval: ask vendors for the clearance number and indication, and distrust AI sold as "analytics" to avoid FDA oversight.
CMS Reimbursement Considerations
Most hospital AI pays back through operations, not separate CMS payment. CMS adds an Electronic Prior Authorization measure for hospitals from the 2027 EHR reporting period (CMS).
State-Level Regulations
California AB 3030, in effect since 1 January 2025, requires a disclaimer and a route to a person on generative AI clinical messages unless a licensed provider reviews them (CDPH, AFL 25-07). Texas SB 1188 (1 September 2025) requires review and disclosure of diagnostic AI, and HB 149 requires notice of AI in treatment from 1 January 2026 (TMLT, 2025); SB 1188 also bars storing Texas patients' EHRs outside the US from 1 January 2026 (McDonald Hopkins).
What does the CMS prior authorization rule require in 2026 and 2027?
CMS-0057-F, finalized in January 2024, requires Medicare Advantage, Medicaid and CHIP payers to decide prior authorization requests within 72 hours for expedited and 7 calendar days for standard requests from 1 January 2026, and impacted payers to run a FHIR Prior Authorization API from 1 January 2027.
Since 2026, payers must also give a specific reason for each denial and post metrics annually, the first set due 31 March 2026; plans on the federal exchanges are excluded from the new clocks (CMS fact sheet). Faster clocks raise the cost of an incomplete submission. A supervised agent that gathers clinicals, drafts and submits the request and chases status, with a person signing off, is a practical first build; our AI automation for healthcare page describes it.
Hospital AI Readiness Checklist (10-Point Self-Assessment)
Score each item 0 to 3. Below 20, do foundational work; 20 to 25, pilot; 26 to 30, implement broadly.
- Data Infrastructure: clean EHR data, extractable through FHIR or vendor APIs.
- IT Staff AI Competency: data engineering skills and capacity to maintain integrations.
- Clinical Champion: a respected physician or nurse advocate.
- Executive Alignment: C-suite agreement and funding.
- ROI Measurement Framework: success metrics defined before deployment.
- Workflow Mapping: decision points and failure modes mapped.
- Change Management Plan: a team and timeline for training and adoption.
- Governance and Oversight: vendor evaluation, pilots, bias audits, monitoring.
- HIPAA and Security Compliance: BAAs, minimum-necessary access, documented controls.
- Patient and Clinician Communication: a plan to explain AI use and escalate concerns.
Facing Data Quality or Integration Challenges?
Gaper's healthcare engineering teams can help you assess your AI readiness and build custom solutions. Bring your score to a free AI assessment.
How Gaper Helps Hospitals Implement AI
Gaper is the AI-native implementation partner that deploys supervised AI agents you own. For hospitals specifically, Gaper's Kelly AI agent addresses one of the highest-ROI use cases: patient scheduling and no-show prediction. Kelly integrates with Epic, Cerner, and other EHRs, learns from your hospital's scheduling and no-show patterns, and automatically flags appointments at high risk of no-show. Hospital operations teams then act on Kelly's predictions by calling patients, offering alternative times, or sending SMS reminders. The result: hospitals report 15% to 35% reductions in no-shows within the first 3 to 4 months. Our Agent Kelly write-up covers clinic-level results.
Beyond Kelly, Gaper's on-demand engineering teams can help hospitals with custom AI implementations. For example, if your hospital wants to build a proprietary clinical decision support tool or integrate multiple AI solutions into your EHR, Gaper can put together a team of engineers with healthcare IT experience. All Gaper engineers are background-checked and experienced in HIPAA compliance, working with healthcare data, and integrating with hospital infrastructure. This is particularly valuable for hospital systems without large internal AI engineering teams, which is the majority of hospitals in the U.S.
Kelly: AI Scheduling That Reduces No-Shows by Up to 35%
Kelly is purpose-built for healthcare scheduling. It ingests historical appointment data, patient characteristics, distance to facility, weather, time of day, and other factors, and predicts which patients are likely to miss their appointment. Kelly then provides real-time risk scores to the scheduling coordinator or access center, who can intervene with targeted outreach. Unlike general scheduling tools, Kelly is designed specifically for healthcare and understands the nuances of healthcare no-shows: pregnant patients have different patterns than orthopedic patients, rural patients have different patterns than urban patients, and so on. Implementation takes 2 to 4 weeks, and ROI is measurable within 2 to 4 months. Cost is transparent: $15,000 to $50,000 upfront plus $5,000 to $15,000 annually.
If your hospital needs custom AI development (e.g., a proprietary algorithm, custom EHR integration, or multi-system implementation), Gaper can put a team on it. All Gaper engineers have background checks, HIPAA training, and experience working with healthcare data. This is a lower-risk alternative to hiring new employees when you need specialized expertise for a time-bound project. For a typical custom AI project, hospitals budget $50,000 to $300,000 in engineering labor.
71%
of acute care hospitals used predictive AI in their EHR (2024, ASTP/ONC)
2-4 Months
ROI timeline for scheduling AI like Kelly
23%
Average no-show rate across 105 studies (Health Policy, 2018)
BAA Available
HIPAA Business Associate Agreement
How long does it take to implement hospital AI?
Implementation time depends on the type of AI and your hospital's readiness. Simple solutions like scheduling AI (Kelly) take 2 to 4 weeks. Clinical documentation AI takes 4 to 6 weeks, and radiology, sepsis and custom builds take 3 to 6 months.
Data quality, interface access and validation set the pace. Budget 20% to 30% of your timeline for testing and clinical validation, even if the vendor says it is not necessary.
What is the typical ROI for hospital AI?
ROI varies dramatically by use case. Scheduling AI (like Kelly) shows ROI in 2 to 4 months and typically delivers 25% to 50% annual ROI. Revenue cycle and documentation tools take 6 to 12 months, and radiology and sepsis 12 to 24.
Those longer ranges are planning estimates. The key is baseline measurement: record your no-show rate, documentation time and denial rate before go-live, or a 9.5% note-time gain is impossible to price.
Is hospital AI safe from a patient safety perspective?
Hospital AI is safe when it is deployed with proper oversight, validation and governance. The gold standard is decision support, where a person verifies the AI's recommendation, rather than autonomous decision-making.
AI does not fatigue, but it can be biased or quietly wrong, as the sepsis validation and scribe omissions show. Require validation data, fairness audits and failure modes, then monitor after go-live, as 79% of predictive AI users do (ASTP/ONC).
What should we ask a vendor before buying hospital AI?
Ask for FDA status, a signed BAA and HIPAA documentation, validation data from hospitals like yours, bias testing, documented failure modes, EHR integration specifics including write access, and customer references you can call.
Also ask about change management costs, ROI guarantees and where data and logs live. For predictive tools, ask for source attributes (training data, intended use, limits). ONC's HTI-1 rule has required certified health IT to support access to these since 1 January 2025; the HTI-5 final rule, released 26 October 2026 and scheduled for Federal Register publication on 28 October, removes that requirement 60 days after publication (HTI-5 final rule; ONC). Do not buy from a vendor who cannot answer clearly and honestly.
How do we ensure clinical staff adoption of hospital AI?
Involve clinicians early, prove value with pilot data before rollout, put the AI inside existing workflows, share validation data and failure modes openly, and name a respected clinical champion for each unit.
Put the tool in screens staff already use, show an audit trail of what it did, and budget for training.
What is the biggest risk in hospital AI implementation?
The biggest risk is deploying AI to solve the wrong problem or without proper change management. A technically sound system fails if it targets a low-priority problem or if clinicians do not trust it.
Confirm the problem costs money or quality before buying, pick problems clinicians care about, pilot, and measure rigorously.
Key Takeaways for Hospital Leaders
AI in hospitals is no longer experimental: 71% of acute care hospitals used predictive AI in 2024. The decision is which applications to prioritize and which vendors to trust.
The hospitals winning with AI treat it as a change management and governance problem, not a technology problem, and start small: a single high-ROI use case (like scheduling AI) in one department, measured, then built on.
Ready to Transform Hospital Operations with AI?
Gaper's healthcare AI experts and Kelly scheduling agent are ready to help you reduce no-shows, cut costs, and improve patient access. The assessment is free. No credit card required. 15-minute consultation with a healthcare AI specialist.
Trusted by healthcare teams at leading hospital systems. HIPAA BAA available. FDA-aligned implementations.
If your healthcare organization needs custom LLM development for EHR integration, data preparation, or specialized clinical NLP tasks, Gaper can assemble a team. Custom models trained on your data. Kelly handles scheduling. Your clinicians focus on patients. Get guidance from our healthcare engineering and compliance experts.
14 verified Clutch reviews. Harvard and Stanford alumni backing. No commitment required.
Thirty minutes, no commitment. We map one workflow, make the build or buy call, and scope the smallest thing worth shipping.
Frequently asked questions
What Is Hospital AI?
What does it take to connect AI to the EHR?
How do clinical NLP and custom LLMs work on EHR data?
What does the CMS prior authorization rule require in 2026 and 2027?
How long does it take to implement hospital AI?
What is the typical ROI for hospital AI?
Is hospital AI safe from a patient safety perspective?
What should we ask a vendor before buying hospital AI?
How do we ensure clinical staff adoption of hospital AI?
What is the biggest risk in hospital AI implementation?
How to Run an AI Agent Pilot That Actually Ships to Production
A practical playbook for running an AI agent pilot that reaches production: scope tight, instrument from day one, and design the handoff before you start.
Mar 21, 2026AI agentsThe State of AI Agents in 2026: What's Actually Working
A grounded look at the state of AI agents in 2026, what reaches production, where pilots stall, and the patterns separating working deployments from demos.
Apr 21, 2026
Multimodal AI: Core Concepts and How it Works?
Ready to turn AI into execution?
Book a free assessment of one workflow. We map it, make an honest build versus buy call before any code, and if an off the shelf product covers the job we will tell you so.